Why Dental Toxins Might Be the Missing Layer in Your Chronic Illness Investigation
When Mercury Shows Up and Changes Everything
What happens when a lab comes back with mercury levels the technician has never seen before?
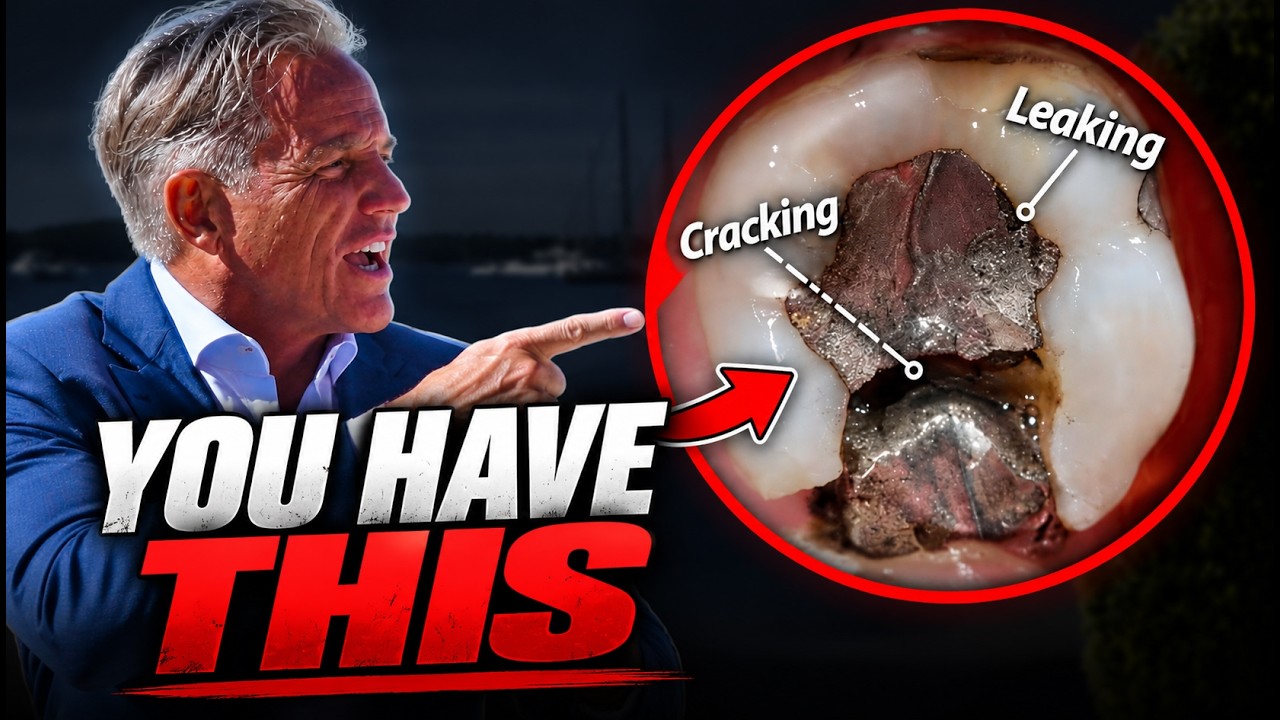
It reframes the entire clinical picture. This conversation opens with exactly that scenario, and the implications ripple outward fast. Mercury toxicity can produce neurological symptoms that look like ALS, multiple sclerosis, or other serious diagnoses without being those conditions at all. The key insight is not just that dental materials can cause problems, but that even when they are not the original trigger for someone's illness, they can keep the nervous system inflamed enough to prevent recovery from progressing. When mold illness, endocrine disruption, and chronic inflammation are already in play, an ongoing mercury burden from dental work can be the variable that makes everything else treatment-resistant.
The Legacy of Dr. Hal Huggins and Treating Dentistry as a Systemic Event
What did Huggins understand that conventional dentistry largely ignored?
That a filling removal is not a local procedure. It is a systemic event that affects biochemistry, autonomic function, and neurological stability. The protocols his work produced treat patients as chronically sensitive individuals whose detox capacity, mineral balance, and nervous system state all matter before, during, and after dental work. The guests describe learning to interpret hair, blood, and urine patterns not as curiosity but as essential clinical context. There is also an honest acknowledgment of the professional risk involved in challenging the official position that amalgam is safe, and the compassion required to serve patients who have been suffering for years without answers.
Why the "Don't Cross the Midline" Rule Exists
What is the logic behind not removing fillings across the midline of the mouth in a single session?
Metal fillings create measurable electrical effects in the mouth, and removing them in a sequence that crosses the midline while a patient is awake may place too much stress on the brain and autonomic nervous system simultaneously. Sedation changes this calculation. Dr. Huggins used EEG monitoring during procedures to watch brain wave patterns shift in real time, which provided direct feedback about neurological stress. For anyone navigating detox and dental revision, these procedural details are not academic. Improper timing and technique can worsen symptoms significantly, while careful protocol design can reduce burden and support neurological stability throughout the process.
What Imaging Can and Cannot Tell You
How reliable is cone beam CT for finding cavitations and jawbone infections?
Helpful but not definitive. Some cavitations and infections do not show clearly on CBCT scans, and confirmation sometimes requires direct clinical evaluation, particularly when symptoms return after a site was previously treated. The most striking clinical stories in this episode involve trigeminal neuralgia resolving after dental intervention, joint pain disappearing after an infected site was addressed, and autoimmune-like flares tied to dead teeth. These are not anecdotes meant to replace diagnosis. They are patterns that point toward asking whether an oral source of inflammation has been properly ruled out.
The Practical Takeaway for Anyone Stuck in Chronic Illness
What is the through line for someone dealing with fatigue, neuropathic pain, detox resistance, or inflammation that will not resolve?
The oral environment deserves serious investigation as a potential upstream driver. Root canals, cavitations, periodontal disease, and incompatible dental materials can each contribute to systemic inflammatory burden in ways that never show up in standard workups. Biological dentistry at its best treats the mouth as part of the whole person, removes interference, and creates conditions where the body's own healing capacity has a genuine opportunity to work.